
Nurse Call & Healthcare contractor resource
Nurse Call System Design Software for Healthcare Plans
Coordinate patient, staff, code, bath, corridor, console, mobile, reporting, network, power, room, integration, testing, and turnover requirements without obscuring clinical workflow. This practical guide explains what to document, how to structure the drawing set, where coordination fails, what the proposal must carry, and how to evaluate software against a real contractor workflow.

What nurse call system design software must solve
Someone searching for nurse call system design software is rarely looking for a generic drawing program. The practical need is a controlled way to translate customer intent and field conditions into a design another estimator, installer, reviewer, programmer, IT administrator, and customer can understand. The software must help the contractor preserve decisions as the project moves from discovery to proposal and from approved scope to installation.
For nurse call & healthcare, the core promise is specific: Coordinate patient, staff, code, bath, corridor, console, mobile, reporting, network, power, room, integration, testing, and turnover requirements without obscuring clinical workflow. That means the plan cannot be an attractive background with unconnected icons. Each important item needs a stable identity and a reason to exist. Its location must agree with schedules and schematics; its infrastructure must be visible; its quantity must reach the estimate; and its open decisions must be owned.
The best result is query-complete rather than keyword-heavy. A customer should be able to use this page to understand the deliverables, ask better questions, recognize missing scope, and select a workflow. A contractor should be able to turn the same guidance into a survey checklist, drawing outline, coordination meeting agenda, estimating review, and acceptance plan.
The design record should answer six groups of questions
The table below connects the design scope to a reviewable output. The exact document set depends on project size, contract, jurisdiction, risk, and the responsible designer. The principle stays the same: put information where it can be checked and cross-reference it with stable identifiers.
| Decision group | What to document | Useful output |
|---|---|---|
| Patient stations, pillow speakers | Patient stations, pillow speakers, call cords, bath/toilet/shower devices, staff presence, code, cancel, dome lights, and room accessories | Healthcare device floor plan |
| Nurse consoles, duty stations | Nurse consoles, duty stations, corridor displays, annunciators, mobile devices, phones, badges, reporting, and administration stations | Room-type device matrix |
| Room controllers, zone controllers | Room controllers, zone controllers, servers, gateways, networks, switches, power supplies, batteries, racks, and licensing | Call-flow/escalation diagram |
| Call types, priorities | Call types, priorities, tones, colors, escalation, routing, assignments, coverage, quiet hours, downtime, reports, and retention | Controller/network/power riser |
| Interfaces to telephony, mobile messaging | Interfaces to telephony, mobile messaging, locating, access control, EHR, beds, televisions, fire alarm, clocks, and other clinical systems | Interface responsibility matrix |
| Cable, pathways | Cable, pathways, infection control, temporary service, programming, testing, inspections, training, documentation, support, and spares | Clinical acceptance and training plan |
Recommended deliverables
Healthcare device floor plan
Healthcare device floor plan. Record the value, source, verification status, responsible party, and revision so another person can audit the decision.
Room-type device matrix
Room-type device matrix. Show the relationship on the correct drawing or schedule instead of burying it in a note that cannot be traced.
Call-flow/escalation diagram
Call-flow/escalation diagram. Separate observed conditions from design assumptions and customer choices; price uncertainty as an allowance or exclusion when needed.
Controller/network/power riser
Controller/network/power riser. Carry stable identifiers into the takeoff, proposal, installation record, test evidence, and closeout documents.
Interface responsibility matrix
Interface responsibility matrix. Review capacity, compatibility, access, serviceability, future change, and failure behavior before the product is committed.
Clinical acceptance and training plan
Clinical acceptance and training plan. Assign ownership at the interface with architecture, electrical, IT, operations, other vendors, and the authority having jurisdiction.
A floor plan is usually the location index, not the entire design. When lines or notes make it hard to answer a question, move the information to the proper schedule, schematic, riser, elevation, matrix, narrative, or calculation worksheet. Then place a clear reference on both documents so the reader can move between them.
Nurse Call & Healthcare project review worksheet
Use these six prompts during discovery, drawing review, estimating, and handoff. Write the answer in project language, identify its source, and mark whether it is verified, selected, assumed, excluded, or assigned to another party.
1. Survey evidence
Review this system-specific scope: Patient stations, pillow speakers, call cords, bath/toilet/shower devices, staff presence, code, cancel, dome lights, and room accessories.
Connect it to this coordination condition: Clinical leadership for workflows, priorities, escalation, response expectations, room use, staffing, downtime, and acceptance. The review is complete only when the plan, Healthcare device floor plan, quantity basis, responsibility, and verification record describe the same decision. If the answer depends on a field condition, product selection, authority, owner policy, or third-party system, name that dependency instead of converting it into an unsupported promise.
2. Drawing decision
Review this system-specific scope: Nurse consoles, duty stations, corridor displays, annunciators, mobile devices, phones, badges, reporting, and administration stations.
Connect it to this coordination condition: Architecture for room types, headwalls, bathrooms, doors, ceilings, millwork, accessibility, infection control, and equipment clearances. The review is complete only when the plan, Room-type device matrix, quantity basis, responsibility, and verification record describe the same decision. If the answer depends on a field condition, product selection, authority, owner policy, or third-party system, name that dependency instead of converting it into an unsupported promise.
3. Infrastructure dependency
Review this system-specific scope: Room controllers, zone controllers, servers, gateways, networks, switches, power supplies, batteries, racks, and licensing.
Connect it to this coordination condition: Electrical for emergency power, circuits, batteries, grounding, panels, receptacles, shutdowns, and temporary conditions. The review is complete only when the plan, Call-flow/escalation diagram, quantity basis, responsibility, and verification record describe the same decision. If the answer depends on a field condition, product selection, authority, owner policy, or third-party system, name that dependency instead of converting it into an unsupported promise.
4. Commercial consequence
Review this system-specific scope: Call types, priorities, tones, colors, escalation, routing, assignments, coverage, quiet hours, downtime, reports, and retention.
Connect it to this coordination condition: IT for networks, servers, virtualization, cybersecurity, identity, integrations, backups, monitoring, patching, and change control. The review is complete only when the plan, Controller/network/power riser, quantity basis, responsibility, and verification record describe the same decision. If the answer depends on a field condition, product selection, authority, owner policy, or third-party system, name that dependency instead of converting it into an unsupported promise.
5. Field verification
Review this system-specific scope: Interfaces to telephony, mobile messaging, locating, access control, EHR, beds, televisions, fire alarm, clocks, and other clinical systems.
Connect it to this coordination condition: Other vendors for beds, television, telephony, mobile messaging, locating, fire alarm, security, EHR, and middleware. The review is complete only when the plan, Interface responsibility matrix, quantity basis, responsibility, and verification record describe the same decision. If the answer depends on a field condition, product selection, authority, owner policy, or third-party system, name that dependency instead of converting it into an unsupported promise.
6. Acceptance evidence
Review this system-specific scope: Cable, pathways, infection control, temporary service, programming, testing, inspections, training, documentation, support, and spares.
Connect it to this coordination condition: Authority, facility standards, approved products, testing, inspections, documentation, staff training, phased occupancy, and support. The review is complete only when the plan, Clinical acceptance and training plan, quantity basis, responsibility, and verification record describe the same decision. If the answer depends on a field condition, product selection, authority, owner policy, or third-party system, name that dependency instead of converting it into an unsupported promise.
Trace one nurse call & healthcare decision through the record
For a renovation of twelve patient rooms and a nurse station in an occupied healthcare unit, use the following chain as a document-control exercise. The entries are not generic fields: each one ties a discipline-specific design question to a deliverable and a commercial or field consequence.
| Design question | Primary record | Traceability test |
|---|---|---|
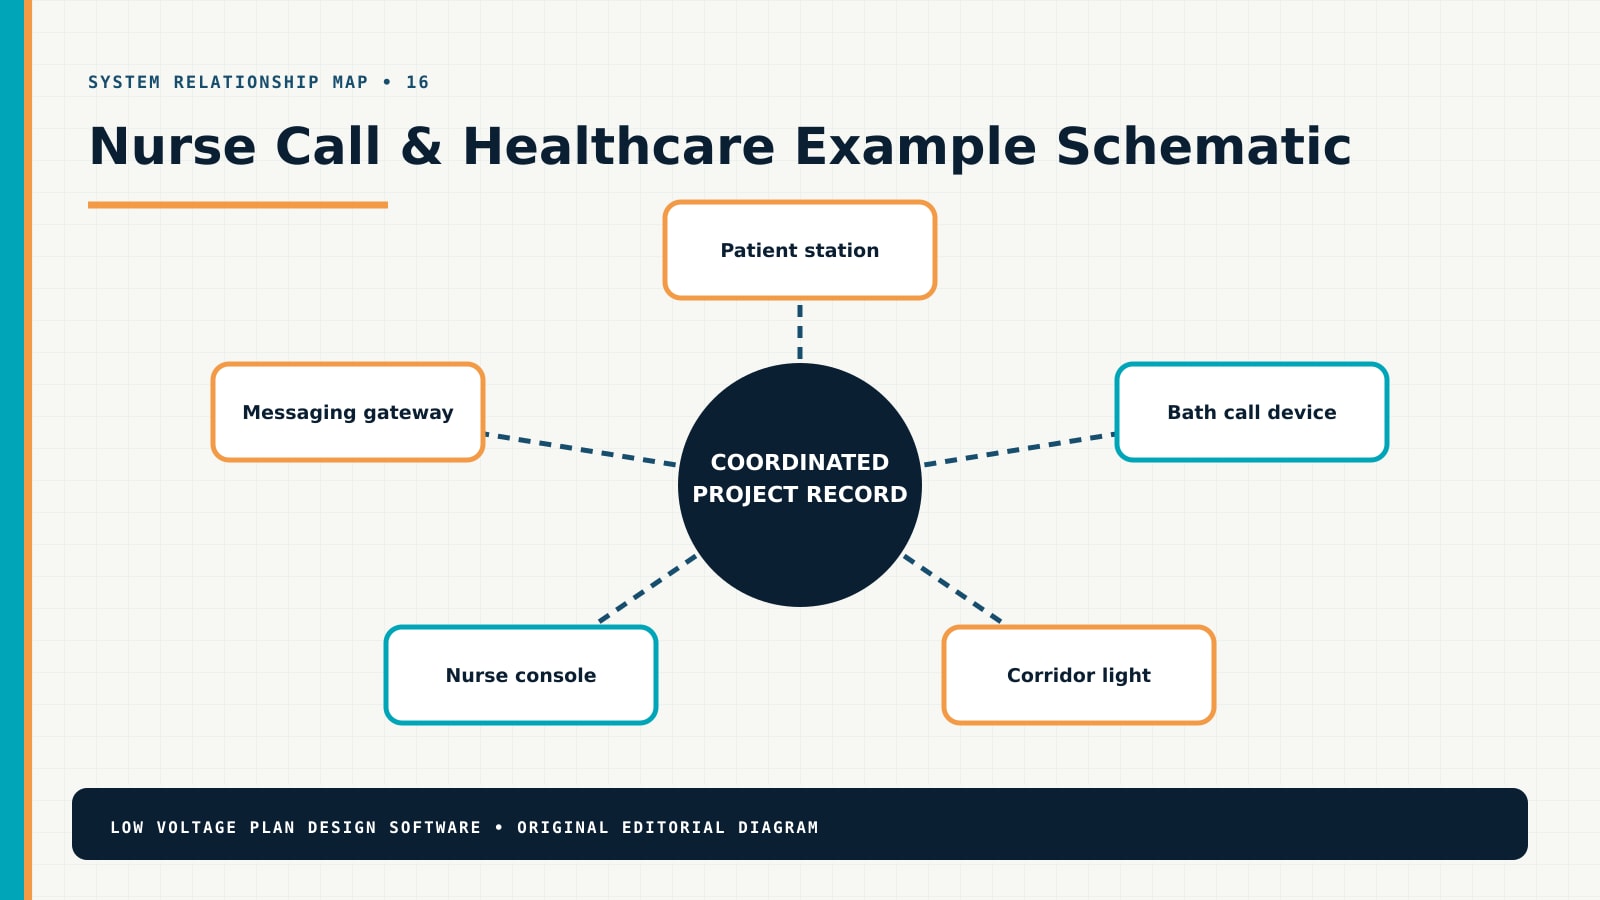
| Patient stations, pillow speakers, call cords, bath/toilet/shower devices, staff presence, code, cancel, dome lights, and room accessories | Healthcare device floor plan | Find the matching Patient station relationship, then identify the quantity, owner, verification status, and effect of a revision to Clinical leadership for workflows, priorities, escalation, response expectations, room use, staffing, downtime, and acceptance. |
| Nurse consoles, duty stations, corridor displays, annunciators, mobile devices, phones, badges, reporting, and administration stations | Room-type device matrix | Find the matching Bath call device relationship, then identify the quantity, owner, verification status, and effect of a revision to Architecture for room types, headwalls, bathrooms, doors, ceilings, millwork, accessibility, infection control, and equipment clearances. |
| Room controllers, zone controllers, servers, gateways, networks, switches, power supplies, batteries, racks, and licensing | Call-flow/escalation diagram | Find the matching Corridor light relationship, then identify the quantity, owner, verification status, and effect of a revision to Electrical for emergency power, circuits, batteries, grounding, panels, receptacles, shutdowns, and temporary conditions. |
| Call types, priorities, tones, colors, escalation, routing, assignments, coverage, quiet hours, downtime, reports, and retention | Controller/network/power riser | Find the matching Nurse console relationship, then identify the quantity, owner, verification status, and effect of a revision to IT for networks, servers, virtualization, cybersecurity, identity, integrations, backups, monitoring, patching, and change control. |
| Interfaces to telephony, mobile messaging, locating, access control, EHR, beds, televisions, fire alarm, clocks, and other clinical systems | Interface responsibility matrix | Find the matching Messaging gateway relationship, then identify the quantity, owner, verification status, and effect of a revision to Other vendors for beds, television, telephony, mobile messaging, locating, fire alarm, security, EHR, and middleware. |
| Cable, pathways, infection control, temporary service, programming, testing, inspections, training, documentation, support, and spares | Clinical acceptance and training plan | Find the matching Patient station relationship, then identify the quantity, owner, verification status, and effect of a revision to Authority, facility standards, approved products, testing, inspections, documentation, staff training, phased occupancy, and support. |
The chain is successful when a reviewer can move in both directions: from a customer outcome to the drawing and proposal, and from a field quantity back to the approved purpose and evidence. If either direction fails, add the missing identity, cross-reference, schedule field, assumption, or responsibility before approval.
A contractor workflow from requirement to accepted scope
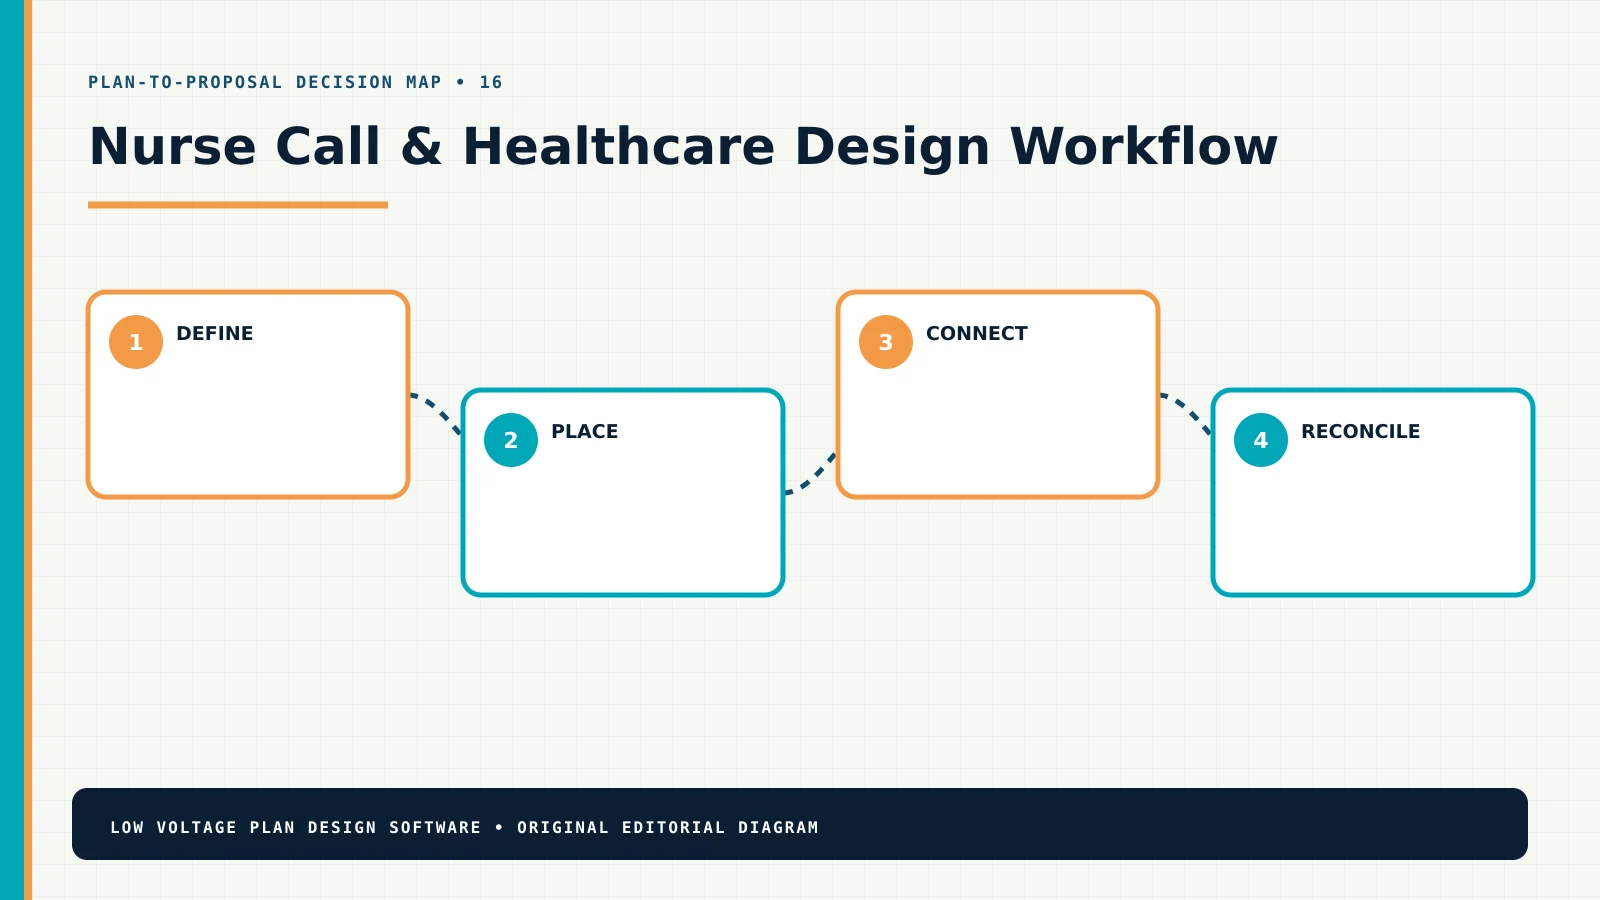
This four-stage sequence keeps design detail proportional to the decision. Early work can show intent and uncertainty. Later work should resolve product-specific interfaces, quantities, installation methods, configuration, testing, and handoff. Do not imply that an early sales layout is permit-ready, engineered, or field-verified unless it actually is.
- Define the operating outcome.Confirm care model, room types, call types, priorities, staff roles, escalation, response, reporting, redundancy, and authority requirements. At this stage, reject anonymous quantities: each important element needs a location, purpose, relationship, status, or documented basis.
- Place and identify the system.Place patient, bath, staff, code, corridor, console, annunciation, mobile, locating, and interface devices by approved room template. At this stage, reject anonymous quantities: each important element needs a location, purpose, relationship, status, or documented basis.
- Connect infrastructure and ownership.Map controllers, stations, networks, gateways, power, batteries, head-end, messaging, telephony, EHR, fire, security, and workflow interfaces. At this stage, reject anonymous quantities: each important element needs a location, purpose, relationship, status, or documented basis.
- Reconcile scope and handoff.Reconcile equipment, cable, licensing, programming, infection-control work, testing, training, records, spares, and proposal scope. At this stage, reject anonymous quantities: each important element needs a location, purpose, relationship, status, or documented basis.
Coordination questions to close before the proposal
Clinical leadership for workflows, priorities, escalation, response expectations, room use, staffing, downtime, and acceptance
Clinical leadership for workflows, priorities, escalation, response expectations, room use, staffing, downtime, and acceptance. Record the value, source, verification status, responsible party, and revision so another person can audit the decision.
Architecture for room types, headwalls, bathrooms, doors, ceilings, millwork, accessibility, infection control, and equipment clearances
Architecture for room types, headwalls, bathrooms, doors, ceilings, millwork, accessibility, infection control, and equipment clearances. Show the relationship on the correct drawing or schedule instead of burying it in a note that cannot be traced.
Electrical for emergency power, circuits, batteries, grounding, panels, receptacles, shutdowns, and temporary conditions
Electrical for emergency power, circuits, batteries, grounding, panels, receptacles, shutdowns, and temporary conditions. Separate observed conditions from design assumptions and customer choices; price uncertainty as an allowance or exclusion when needed.
IT for networks, servers, virtualization, cybersecurity, identity, integrations, backups, monitoring, patching, and change control
IT for networks, servers, virtualization, cybersecurity, identity, integrations, backups, monitoring, patching, and change control. Carry stable identifiers into the takeoff, proposal, installation record, test evidence, and closeout documents.
Other vendors for beds, television, telephony, mobile messaging, locating, fire alarm, security, EHR, and middleware
Other vendors for beds, television, telephony, mobile messaging, locating, fire alarm, security, EHR, and middleware. Review capacity, compatibility, access, serviceability, future change, and failure behavior before the product is committed.
Authority, facility standards, approved products, testing, inspections, documentation, staff training, phased occupancy, and support
Authority, facility standards, approved products, testing, inspections, documentation, staff training, phased occupancy, and support. Assign ownership at the interface with architecture, electrical, IT, operations, other vendors, and the authority having jurisdiction.
Coordination is part of the product. A device may be inexpensive while its pathway, power, network, mounting, licensing, access, programming, firestopping, outage window, or third-party interface carries the real cost. The drawing set should expose those dependencies early enough for a responsible party to answer them.
Worked example: a renovation of twelve patient rooms and a nurse station in an occupied healthcare unit
Starting problem. Room templates differ, existing circuits and cabling are uncertain, and clinical staff require uninterrupted call coverage while devices and head-end components are replaced.
Design response. The design creates room-type matrices, maps each call and escalation path, identifies temporary service, separates verified conditions from field checks, and assigns interface testing.
Commercial and field result. The contractor can phase the work and price risk explicitly while clinical leadership reviews exactly how every call is initiated, displayed, routed, cleared, recorded, and restored.
The example is not a product recommendation or a quantity template. Its value is the reasoning chain: define the operating outcome, identify what is verified, document relationships, expose dependencies, and reconcile the resulting work to an issued revision. Reuse that method, but verify every location, dimension, product, code requirement, pathway, calculation, and responsibility on the actual project.
Example review checkpoints
- Can a reviewer explain why every major element exists and which customer outcome it supports?
- Can an estimator trace every major quantity to a plan, schedule, schematic, calculation, allowance, or explicit assumption?
- Can a field technician distinguish approved work, alternates, owner-furnished items, existing conditions, demolition, and unverified conditions?
- Can IT, electrical, architecture, operations, and other vendors see their interfaces without interpreting hidden design intent?
- Can the team record a change once, identify affected documents and quantities, obtain approval, and preserve the prior revision?
- Does the acceptance plan test operating outcomes and interfaces instead of confirming only that devices power on?
How to evaluate nurse call system design software
Use a representative project instead of a polished demonstration. Recreate a real survey condition, one shared infrastructure dependency, one customer change, and one scope alternative. The evaluation should expose whether the tool supports decisions or simply makes drawing faster.
| Test | What good looks like | Warning sign |
|---|---|---|
| Baseline and revisions | Rooms, scale, field evidence, assumptions, issue status, and revisions remain visible and controlled. | A new background or duplicate file silently breaks identities and quantities. |
| Industry documentation | Plans, schedules, schematics, details, notes, and responsibility fields match the discipline. | Generic icons substitute for system relationships and deliverables. |
| Quantity traceability | Equipment, accessories, cable, infrastructure, licenses, labor, and options trace to the approved revision. | The estimate is a separate list that cannot be reconciled to the plan. |
| Customer scope | Inclusions, exclusions, allowances, alternatives, prerequisites, and decisions are understandable. | The proposal promises performance while hiding assumptions and third-party work. |
| Field handoff | Technicians receive stable IDs, current documents, verification items, change control, test expectations, and closeout structure. | Installers work from screenshots or sales notes without revision status. |
| Connected workflow | The plan can support proposal, follow-up, approval, change, and closeout without retyping the project. | Every workspace recreates customer, location, item, quantity, and status data. |
Common failure modes
- Device-count design: a quantity is selected before purpose, geometry, interfaces, or infrastructure are understood.
- Decorative schematic: lines show that boxes connect but omit ports, media, direction, protocol, power, ownership, or failure behavior.
- Invisible shared scope: racks, network, power, pathways, accounts, licensing, programming, and testing are assumed rather than assigned.
- Revision drift: plan, schedule, BOM, proposal, installer copy, and closeout record describe different versions of the project.
- False precision: unmeasured routes, unverified conditions, preliminary models, or early product choices are presented as confirmed facts.
- Weak acceptance: completion means “installed” instead of verified operating outcomes, interfaces, training, documentation, and owner approval.
Focused Nurse Call & Healthcare field answers
Use these two query-specific resources when the broad workflow is not enough. Each answer includes a contractor method, worked situation, unique diagram, proposal audit, internal reading path, authoritative references, and a direct connection back to this industry workflow.
Nurse Call Room and Device Schedule for Healthcare Coordination
Coordinate each patient, toilet, corridor, staff, duty, code, pillow-speaker, annunciation, and interface endpoint with room function, call type, priority, power, network, cable, and test.
Nurse Call Infrastructure Checklist: Network, Power, Pathways and Interfaces
Define the rooms, head end, controllers, network, power, UPS, clocks, mobile integration, interfaces, cabling, pathways, cybersecurity, commissioning, and clinical ownership that make endpoint plans work.
Continue the research inside this publication
This canonical page is the industry entry point. Use the related resources below to move from selection into specific drawings, schedules, examples, and workflows. The links use adjacent search language intentionally so readers can follow the problem rather than return to a generic archive.
- nurse call coordination guide — use it to extend this page into the next documented decision.
- cable schedule guide — use it to extend this page into the next documented decision.
- telecom-room guide — use it to extend this page into the next documented decision.
- multi-discipline hub — use it to extend this page into the next documented decision.
- floor-plan workflow — use it to extend this page into the next documented decision.
Compare this discipline with all 22 low-voltage industry design software workflows, or start from the broader low-voltage disciplines hub. Use the design guides for methods, the plan examples for scenarios, the planning tools for transparent calculations, and the glossary for shared terminology.
Authoritative references to verify for this project
These links are starting points, not substitutes for the adopted code, contract documents, manufacturer instructions, licensed design, or authority approval. Confirm current editions, jurisdiction, product applicability, and project-specific requirements.
- UL Healthcare Certifications — healthcare product and system safety context.
- HHS Health Industry Cybersecurity Practices — healthcare cybersecurity practices.
- FGI Guidelines — healthcare facility design guidance context.
Frequently asked questions
What should nurse call system design software produce?
It should produce more than a diagram. A useful project record connects locations, identifiers, system relationships, schedules, infrastructure, assumptions, quantities, scope boundaries, review decisions, field changes, testing, and closeout evidence. For this discipline, the minimum useful set normally includes Healthcare device floor plan, Room-type device matrix, Call-flow/escalation diagram, Controller/network/power riser.
Can the software replace engineering, code review, or manufacturer design?
No. Documentation software helps a qualified team organize, communicate, reconcile, and revise the work. It does not grant a license, determine the adopted code, approve a regulated design, validate a proprietary calculation, or replace manufacturer instructions and authority review.
How should a contractor compare nurse call & healthcare design tools?
Test the real workflow. Begin with a survey change, place and identify representative elements, build a schedule or schematic, revise a shared dependency, reconcile quantities, produce customer-readable scope, and inspect the field handoff. A polished symbol library is not enough if identities, relationships, quantities, revisions, and approvals fall apart.
What information belongs on the floor plan?
Keep location-specific information on the plan: room, device or endpoint position, purpose, stable ID, mounting or orientation intent, nearby constraints, and cross-references. Move repeated attributes to schedules and system relationships to a riser, one-line, topology, signal flow, control diagram, or responsibility matrix.
How does this improve the proposal?
The proposal becomes explainable because devices, accessories, cable, infrastructure, licenses, labor, programming, testing, training, allowances, alternatives, and exclusions trace back to an approved design revision. When the drawing changes, the team can find the commercial effect instead of relying on memory.